The Most Frequent Problems with Dental Crowns and How to Avoid Them

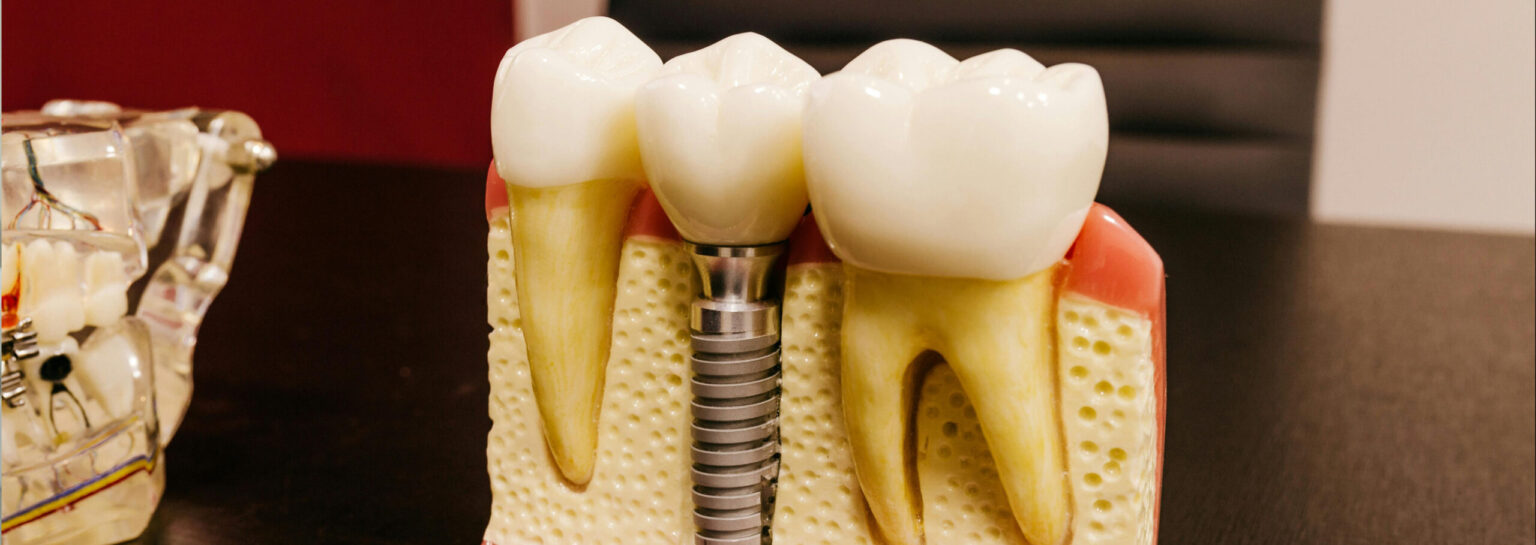

Dental crowns solve a very practical problem. When a tooth is too damaged for a simple filling but still worth saving, a crown can restore its shape, strength, and appearance. In daily practice, they are one of the most useful tools dentistry has. A good crown can let someone chew comfortably, protect a cracked tooth from splitting further, hold a weak tooth together after root canal treatment, or improve a tooth that has become badly worn down.
That said, crowns are not magic. They are restorations, not replacements for biology. The tooth underneath is still alive in many cases, the gum around it still reacts to irritation, and the bite still has to function under real chewing forces. When patients say, “I thought the crown meant the tooth was fixed forever,” the conversation usually becomes less about the crown itself and more about expectations, maintenance, and the details of how crowns succeed or fail over time.
Most crown problems are preventable, or at least manageable if caught early. The key is understanding where things go wrong. Some issues begin with the condition of the original tooth. Others come from bite forces, clenching, oral hygiene, diet, or simple wear over years. A few are linked to the fit or design of the restoration. None of this means Dental Crowns are unreliable. It means they do best when planning, placement, and aftercare are all taken seriously.
A crown can only be as good as the tooth it sits on
This is one of the most important truths about crowns, and patients often hear it too late. A crown covers and reinforces a tooth, but it does not make a compromised foundation healthy by itself. If the remaining tooth structure is thin, decayed, cracked below the gumline, or difficult to isolate during treatment, the long-term outlook changes.
Picture two different cases. In the first, a molar has one old large filling with a fracture line across a cusp, but there is still plenty of sound tooth left. In the second, the same molar has had several fillings, recurrent decay under one side, and only narrow walls remaining. Both may receive crowns, but the second tooth has a much smaller margin for error. The crown can still work well, but the risk of future problems is higher from day one.
That is why good diagnosis matters more than many people realize. Before a crown is placed, the dentist is thinking about how much healthy tooth remains, whether the tooth is cracked, whether the gum and bone support are stable, whether root canal treatment is needed, and whether the bite will overload the final restoration. Skipping that careful planning is one reason crown problems show up sooner than expected.
Sensitivity and pain after a crown
Some tenderness after a new crown is common, especially for the first few days. The tooth has been prepared, the gum may be slightly irritated, and the bite is adapting to a new surface. Mild temperature sensitivity or soreness when biting can settle as the area calms down. Persistent pain is different.
One frequent problem is a high bite. Even a tiny discrepancy can matter. Teeth meet with remarkable precision, and a crown that is just slightly too tall may take more force than the surrounding teeth every time a person bites down. Patients often describe this as a tooth that feels “first” when they close, or a crown that feels subtly intrusive even if they cannot explain why. Left uncorrected, that pressure can lead to ligament inflammation, soreness on chewing, headaches, and in some cases a cracked porcelain surface or stress on the supporting tooth.
Another source of post-crown Dental Crowns omnidentalspecialty.com pain is pulp irritation. Even when a tooth did not need root canal treatment before the crown, the preparation can sometimes aggravate an already stressed nerve. Deep old fillings, prior trauma, repeated dental work, or cracks all increase that risk. Sometimes the nerve settles. Sometimes it does not, and the tooth later requires root canal treatment through or around the new crown.
Temperature sensitivity can also point to an issue with the margins, cement seal, or exposed root surfaces near the gumline. If the discomfort is sharp, getting worse, or lasting beyond the normal adjustment period, it should not be watched indefinitely.
Loose crowns and crowns that come off
A crown that comes loose can feel dramatic, but the underlying reason is often straightforward. The crown may have lost retention because the cement has broken down over time, the underlying tooth has decayed, or the original shape of the prepared tooth did not provide ideal grip. In some cases, sticky foods simply exploit a weakness that was already there.
Not every dislodged crown means the treatment failed. If the crown itself is intact and the tooth underneath is healthy, recementation may be possible. The concern is what caused the loosening in the first place. A crown that repeatedly comes off usually has an underlying design or structural problem. Sometimes there is not enough tooth height remaining to hold it securely. Sometimes the preparation is too tapered. Sometimes recurrent decay has changed the fit. Sometimes heavy grinding places repeated lifting and twisting forces on the crown until the cement gives way.
Temporary crowns come off more often than permanent ones, and that is by design to some extent. They use weaker cement so they can be removed easily. But if a temporary crown is off for too long, teeth can shift surprisingly quickly, and the final crown may no longer fit as intended. That is a small timing issue that can turn into a very frustrating remake.
Decay at the crown margin
This is one of the most common reasons crowns need replacement. Patients are often surprised by it because they assume a crowned tooth cannot get a cavity. The crown material itself does not decay, but the natural tooth around the edge absolutely can.
The margin, where the crown meets the tooth, is the critical zone. If plaque sits there consistently, or if the fit is not ideal, bacteria can work into that junction. Recurrent decay often begins quietly. There may be no pain at first. The crown can look acceptable from above while the margin is failing underneath. By the time symptoms appear, the tooth may need much more than a simple repair.
Back teeth are especially vulnerable when flossing is inconsistent or the area traps food. Sugary snacks and frequent acidic drinks add to the risk, but the bigger factor in many cases is not dramatic diet, it is everyday plaque control around difficult-to-clean edges. A crown with a bulky contour or a suboptimal contact point can make home care harder, which is why contour and polish matter more than patients tend to notice.
This is also where patients with dry mouth run into trouble. Reduced saliva from medication, age-related changes, or certain medical treatments raises the cavity risk Dental Crowns around crown margins significantly. A beautifully made crown can still fail early in a very dry mouth if prevention is not adjusted to match the risk.
Chipped porcelain and fractured crowns
Not all crown materials behave the same way. Porcelain and ceramic crowns can look excellent, especially in visible areas, but they can chip or fracture under certain conditions. Molars in patients who clench or grind are a classic example. The crown may be well made and well fitted, yet years of nighttime pressure can create tiny cracks that eventually turn into a visible chip.
Sometimes the issue is impact rather than wear. Biting unexpectedly on a hard olive pit, ice, popcorn kernel, or fork can damage even a strong restoration. Occasionally the fracture reflects a design problem, such as porcelain being too thin in a high-stress area or unsupported by the underlying structure.
The choice of material matters. Zirconia tends to be very strong, metal-ceramic crowns have a long track record, and all-ceramic options can be excellent for esthetics, but none are universally best for every tooth. The right crown depends on where the tooth is, how much load it takes, whether the patient grinds, how much space exists between the jaws, and how important translucency is for appearance.
A front tooth crown has a different job than a molar crown. That sounds obvious, but many crown problems can be traced back to treating all teeth as if they function under the same demands. They do not.
Gum irritation and bleeding around crowns
A crown should not make the gums angry. When gums stay red, puffy, or bleed around a crowned tooth, something is usually off. The cause may be oral hygiene, but not always. Overcontoured crowns, rough margins, excess cement left below the gumline, or an edge that invades the biologic space can all trigger chronic inflammation.
Patients often blame themselves first. Sometimes they are right, especially if flossing has become irregular because the area snags or feels awkward. But if a patient says, “I clean it every day and it still bleeds around that one crown,” that deserves a close look. A well-contoured crown should allow the gum to sit comfortably against it and should permit normal cleaning.
Poorly shaped crowns can also create food traps. Food packing between two teeth is not just annoying. It can inflame the gum, contribute to bone loss over time, and increase decay risk on the neighboring tooth as well. Contacts that are too open or too heavy both create trouble, just in different ways.
The gum around a crown often tells the truth before the tooth does. Persistent bleeding, tenderness, or a bad taste around one restored tooth should not be dismissed as minor.
Dark lines, poor color match, and cosmetic disappointment
Not every crown problem is painful. Some are aesthetic, and these matter more than people sometimes admit. A front crown that looks flat, opaque, too long, too short, or slightly gray near the gum can affect confidence every day.
Older porcelain fused to metal crowns sometimes develop a dark line near the gum margin as gums recede. This is not always a sign of disease, but it can be cosmetically unacceptable, especially in the smile zone. Even all-ceramic crowns can disappoint if the shade match is off or if the adjacent teeth were not evaluated carefully under proper lighting.
Natural teeth are more complex than “white.” They have translucency, texture, tiny asymmetries, and age-related character. A crown that is technically sound but too uniform can stand out immediately. That is why photography, shade mapping, and communication with the laboratory matter so much for visible teeth.
Cosmetic problems are also more likely when the surrounding gums are uneven or when one tooth is being restored in isolation while neighboring teeth have wear, staining, or crowding. The best looking result is often the one that accounts for the whole smile, not just the single tooth.
Cracks in the tooth under the crown
This is one of the most frustrating scenarios because the crown may still look intact while the tooth underneath develops a fracture. Crowns can help protect cracked teeth, but they do not guarantee that a crack will stop progressing, especially if it extends deep or if biting forces remain high.
Patients with untreated clenching habits are at particular risk. They may crack natural teeth, fillings, and crowns alike. A night guard is not glamorous, but it can make the difference between a crown lasting many years and a crown placed on a tooth that later splits. Once a fracture extends into the root in a way that cannot be predictably managed, the tooth may be lost despite prior crown treatment.
There is also a judgment call involved before crowning a tooth that may already be cracked. Some cracks are restorable. Others carry a guarded prognosis from the start. Honest discussion at that stage prevents a lot of disappointment later. A crown can be the right treatment and still come with uncertainty if the underlying crack pattern is suspicious.
When a crowned tooth needs root canal treatment later
This surprises patients more often than almost any other crown issue. A crown does not eliminate the chance that the nerve inside the tooth may become inflamed or die later. In fact, heavily restored teeth are already under more stress than untouched teeth.
A tooth that has had repeated fillings, deep decay, trauma, or extensive reduction for a crown can later develop irreversible pulpitis or necrosis. The timing varies. It may happen within weeks, or years later. Sometimes the trigger is obvious, such as a deep pre-existing condition. Sometimes the tooth was borderline and simply declared itself over time.
Treating a root canal through an existing crown is often possible, but it is not ideal in every case. The access opening can weaken certain crown designs, and a final repair must be sealed properly. In some situations, especially when the crown already has age, wear, or marginal concerns, replacement after root canal treatment makes more sense.
That does not mean the crown caused the problem. Often, the tooth was already compromised enough that the chance of future nerve issues was part of the original risk profile.
The warning signs that deserve attention
Some crown issues are minor and self-limiting. Others should be examined promptly because early intervention can preserve both the crown and the tooth.
- Pain when biting that lasts more than a few days
- A crown that feels loose, rocks, or lifts with sticky food
- Bleeding gums around one crowned tooth despite regular cleaning
- Temperature sensitivity that is getting worse rather than better
- Food trapping, bad taste, or a smell coming from the area
Patients often wait because the discomfort is intermittent. That delay can be costly. A small margin leak is easier to manage than advanced decay under an existing crown. A bite adjustment is simpler than months of overloading a tooth until it becomes cracked or chronically inflamed.
How to avoid most crown problems before they start
A successful crown begins long before cementation. It starts with diagnosis, then material selection, then precise tooth preparation, accurate impressions or scans, thoughtful provisionalization, and a final fit that respects both the bite and the gum tissue. The patient plays a large role too.
One practical mistake is choosing speed over planning. Same-day crowns can be excellent in the right hands and the right cases, but not every tooth is an ideal candidate for a rushed workflow. Complex bites, cosmetic front teeth, and teeth with uncertain cracks may benefit from a more deliberate process. Fast is not always careless, but efficiency should not crowd out judgment.
Home care is equally important. Patients sometimes brush well but neglect flossing because they assume the crown has “sealed” the tooth. The opposite mindset is more useful. Crowned teeth deserve more attention at the margins, not less. Interdental cleaning, fluoride exposure, and management of grinding habits often determine the lifespan of Dental Crowns more than the brand of ceramic ever will.
The strongest prevention habits are not complicated, but they need consistency:
- Brush carefully along the gumline twice a day with fluoride toothpaste
- Clean between the teeth daily with floss or another interdental aid that actually fits
- Use a night guard if you clench or grind, especially after crowns on back teeth
- Keep recall visits and X-rays on schedule so small margin issues are caught early
- Avoid chewing ice, hard pits, and other habits that create sudden point pressure
For patients with dry mouth or high cavity risk, prevention needs to be intensified. That may include prescription fluoride, saliva substitutes, more frequent hygiene visits, or dietary coaching that focuses on frequency of sugar exposure rather than only the total amount. A patient sipping sweetened coffee all morning can create more trouble around crown margins than someone who eats dessert with dinner and then cleans their teeth properly.
The role of bite, and why tiny adjustments matter
Bite problems are underestimated because they are hard to see without training. A crown can look beautiful on an X-ray and still feel wrong in function. One high contact on a molar can concentrate force dramatically. Patients may describe a sensation of “pressure” rather than pain, or they may start chewing on the other side without realizing it.
Over time, an imbalanced bite can contribute to soreness, mobility, gum recession, porcelain wear, and even fractures. This is especially true in patients who already have worn teeth, missing teeth, or a history of jaw clenching. A single crown placed into an unstable bite becomes part of a larger mechanical system. If the overall system is off, the crown absorbs some of that dysfunction.
This is why a careful bite check matters at delivery and again if symptoms linger. Many post-crown comfort problems improve quickly once a precise adjustment is made. Patients sometimes feel guilty returning for what seems like a small annoyance. They should not. Small bite corrections are part of doing crown work properly.
Temporary crowns are not a casual phase
The period between tooth preparation and final cementation can influence the outcome more than people expect. A temporary crown protects the tooth, preserves spacing, helps the gum tissue shape itself, and lets the patient test basic comfort and appearance. When a temporary breaks, leaks, or comes off repeatedly, it is not just inconvenient. The tooth can become sensitive, drift, or develop inflamed gums that complicate the final fit.
Some of the best final crown results are helped by a well-made temporary. This is particularly true for front teeth, where contour, length, and gum response provide useful information before the definitive crown is fabricated. Patients who report that the temporary feels too bulky, catches on the bite, or irritates the gum are giving valuable feedback, not complaining unnecessarily.
How long crowns really last
Patients often ask for a number, and it is understandable. The honest answer is that crown longevity varies widely. Many crowns last well over a decade. Some fail much earlier. A few remain serviceable for far longer than expected. The spread depends on the original tooth condition, crown material, bite forces, oral hygiene, diet, dry mouth, smoking, gum health, and the quality of both placement and maintenance.
What shortens crown life most often is not dramatic trauma. It is the quiet accumulation of stress and neglect. A little plaque at the margin, a little grinding at night, a missed recall, a small open contact that keeps packing food, a slightly high bite that no one revisits. None of these sound catastrophic in isolation. Together, they can turn a good restoration into an early replacement case.
Patients should think of crowns the way they think of tires or roofing. Excellent materials help, but lifespan depends heavily on conditions and upkeep. That mindset leads to better decisions and fewer surprises.
Choosing the right dentist and asking the right questions
Most patients are not in a position to judge margin quality or occlusal design, but they can ask sensible questions. If a tooth is badly broken down, it is reasonable to ask how much healthy tooth remains and what the long-term outlook is. If you grind, say so. If the crown is for a front tooth, ask how shade selection and esthetic planning will be handled. If you have dry mouth, high cavity history, or gum disease, bring that into the discussion because it changes the prevention plan.
A thoughtful clinician will usually explain not just the procedure, but the specific risks that apply to your tooth. That conversation matters. The crown on a heavily restored lower molar in a grinder is not the same proposition as a crown on a relatively intact premolar with a stable bite. Good dentistry lives in those distinctions.
Dental Crowns remain one of the most reliable ways to save compromised teeth, but reliability is not the same as invulnerability. The most frequent problems, sensitivity, loosening, decay at the margin, chipping, gum irritation, bite issues, and later nerve trouble, tend to follow predictable patterns. When those patterns are understood early, most can be reduced, managed, or avoided outright. The crown matters, but the surrounding biology, the bite, and the habits that follow matter just as much.
Omni Dental Specialty
1690 E Gonzales Rd, Oxnard, CA 93036, United States
+1 805-410-9603
FAQ About Dental Crowns
How long do crowns last on teeth?
A dental crown often lasts about five to fifteen years, although some last longer. Material, the underlying tooth, oral hygiene and grinding habits affect longevity. Regular dental examinations help identify wear, decay or a loose crown; no lifespan is guaranteed.
How much does a tooth crown cost?
There is no single price for every crown. Material, laboratory work, the condition of the tooth and any additional treatment affect the fee. Ask for a written estimate and confirm your insurance benefits, exclusions and out-of-pocket costs before treatment.
What is the downside of crowns on teeth?
A conventional crown usually requires irreversible removal of some tooth structure. Possible problems include sensitivity, chipping, loosening and decay at the crown margin; some teeth later need root canal treatment. Discuss your tooth's condition, material choices and suitable alternatives with your dentist.